Lessons learned about survival of structures during Waldo Canyon Fire

Lessons Learned from Waldo Canyon Fire
Lessons Learned from Waldo Canyon Fire, cover. Click to enlarge

The Fire Adapted Communities Coalition has prepared an excellent report titled “Lessons Learned from Waldo Canyon”. Written by representatives from the Insurance Institute for Business and Home Safety, U.S. Forest Service, International Association of Fire Chiefs, and the NFPA, it documents factors that affected the destruction or survival of structures during the Waldo Canyon Fire, a fire that destroyed 346 Colorado Springs homes in June of 2012. This document, along with the Texas report, “Common Denominators of Home Destruction”, could be very useful resources for communities and home owners that desire to mitigate potential damage before wildfires threaten their wildland-urban interface.

Often you will see media reports using words like “random” or “miracle” to describe how some homes are burned while others survive a wildfire that burns into a community. It is neither — it is science — and fuel reduction, building materials, screening off vents, plugging holes between roof tiles, a lack of combustible decks, the actions your neighbor takes or does not take, and many other factors. And did I mention fuel reduction?

While the city of Colorado Springs and their fire department has received criticism for their lack of operational preparedness and training for wildfires, as well as their actions during the Waldo Canyon Fire, this report indicates the city had a program that resulted in some positive outcomes related to fuel mitigation and home owner education about how to reduce the chances of structures burning during a wildfire event.

Here is a sample of some of the conclusions identified in the report:

Observations on building design and materials improvements and maintenance could have reduced losses:

  • Ember ignition via ignition of combustible materials on, in or near the home was confirmed by the surveys. This reaffirms the serious risk posed by ember ignitions to properties during wildfires. This reinforces the importance of maintaining an effective defensible space and regularly removing debris from areas on and near the home.
  • Home-to-home fire spread was again a major issue, as with prior post-fire field investigations. When it occurred, it was dependent on at least one wildland fire-to-home ignition and then home spacing and slope / terrain. Home-to-home fire spread was attributed to a relatively large number of home losses in this survey.
  • Wildland fire-to-home ignition was influenced by location of home on slope and fuels treatment(s) or lack of on the slope leading to the home.
  • A building can be hardened with noncombustible materials, for example, but it is also necessary to incorporate appropriate construction details, which will help ensure that the protections offered by those materials is not by-passed.
  • Individual homeowners must take responsibility for fortifying their property against wildfire damage by taking appropriate measures to incorporate noncombustible building materials and construction details.

Observations on the role of fuels management and landscape vegetation and features:

  • Past fuel treatments by mastication in heavy, continuous, mature Gambel oak retained multi-season effectiveness for reducing wildfire spread. Two- and three-year-old oak treatments did not carry fire. Oak leaves were scorched, but did not typically burn.
  • Hardened landscape barriers such as noncombustible retaining walls, paths and gravel borders were effective in stopping fire in lighter fuel types.
  • Pruning and thinning of ladder fuels in Gambel oak clumps, as a Firewise practice by homeowners, appeared to be effective in keeping fire on the ground and reducing crown fire potential.
  • Firewise landscape plants, primarily deciduous trees and shrubs, were scorched but did not burn when exposed to heat from adjacent crowning fuels.
  • Landscaping fencing contributed to fire spread from adjacent native areas to structures. Split rail and cedar privacy fencing both led fire to structures.

The video below is very well done.

More information on Wildfire Today about the Waldo Canyon Fire.

Escape from the Pagami Creek Fire

Pagami Creek fire, burns along lake shore
Pagami Creek fire burns along lake shore in undated photo by Superior National Forest

Outside Magazine has a riveting article about Greg and Julie Welch who had to flee in their kayaks as the massive wind-blown Pagami Creek Fire consumed tens of thousands of acres in the Boundary Waters Canoe Area Wilderness in Minnesota on a September day in 2011.

When lightning ignited the fire on August 18, the Superior National Forest made a decision to not suppress it, but to herd it around as necessary to keep it within a reasonable maximum management area while allowing natural processes to do their thing. After 12 days it had only grown to approximately 130 acres, and fire management officials may have thought things were going well — until September 12 when everything went to hell. Strong winds gusting at 35 mph or more spread the fire 16 miles to the east, ultimately burning over 92,000 acres by mid-October. HERE are some of the posts on Wildfire Today about the Pagami Creek Fire.

Greg Welch had been a photojournalist and often had taken photos of wildland firefighters as they suppressed fires, so when rangers told him about the Pagami Creek Fire, both he and the rangers thought their camping plans sounded reasonable, since the fire was miles away.

On the second day of their trip, the Welchs paddled their kayaks to another camping spot and set up their tent. Soon, and very unexpectedly, the fire was on them, and they hurriedly took some belongings to their kayaks and prepared to get out into the lake. Here is an excerpt from the Outside article:

…Julie was sitting in her kayak, watching her husband run down to the shore. Just as he came down the slope, the fire crested over the bank and roared just a few feet behind him. Greg threw the life jacket to Julie and told her to go while he strapped the last bags onto his kayak and dragged it to the water.

As Julie paddled out, everything suddenly went black as the fire pushed a thick cloud of soot and ash ahead of it. She couldn’t see Greg, so she screamed his name, but the noise of the fire was like standing next to a freight train. All she could see was thick smoke and burning trees falling in the water. For a few seconds, she thought Greg was lost, and that she was, too. She had no map, and no way to get back alone.

Then Greg appeared, paddling out of the smoke, a few feet away from her. But just as soon as she caught sight of him, the wind tossed her kayak into the air and flipped her into the cold water. By the time she surfaced, the boat had been blown far across the lake. Greg paddled toward her, but the wind was too strong—he couldn’t stop—and it blew him right past her. So he jumped in the water, holding his kayak and staying still, yelling for her to swim toward him. It took a few minutes for Julie to reach him, but together they clung to his boat while everything around them burned.

In addition to Greg and Julie Welch, eight U.S. Forest Service employees had near misses and entrapments on the fire. There is an  an excellent facilitated learning analysis about them being caught out in front of the rapidly spreading fire in canoes while trying to evacuate the recreating public from the area. At one point when they were fleeing the fire, the smoke was so thick they could not see the fronts of their canoes. Two people bailed out of a canoe to take refuge in the cold water, deploying a single fire shelter over their heads as they floated, suspended by their life jackets. Two others were flown out at the last minute by a float plane when the pilot somehow found a hole in the smoke and was able to find them, land on the lake, and extract them. Four people, after paddling furiously in the strong winds, dense smoke, and darkness, unable to find a fire shelter deployment site on the heavily forested islands, finally found a small, one-eighth acre barren island where they climbed inside their shelters as they were being pounded with burning embers.

Using escaped prescribed fire reviews to improve organizational learning

Results have been released for an evaluation of the review process for escaped prescribed fires to attempt to determine if reviews are contributing to or inhibiting achievement of organizational learning. The entire report is here, and below is a very brief summary provided by the Joint Fire Science Program:

****

RESULTS: Based on conversations in a series of workshops and follow-up interviews, researchers identified several elements of the review process that best facilitate organizational learning:

Local Leadership: The local leader sets the tone for creating a learning environment in the unit. When an escape does occur, involving the local fire leadership in a discussion about the purpose and process of a review can dramatically improve the local learning environment.

Review Team: Review team members act as witnesses and facilitators to first help the local unit make sense of what they experienced. They do this by providing for psychological safety and by emphasizing listening without judgment.

Boundary Management: Boundaries for information that should be shared and not shared, and with whom, are continually identified and respected.

Transfer: The learning modalities need to simulate the spaces of action in which people actually work.

Follow Through: Just as a burn plan needs to account for mop-up and monitoring, so does the review of an escape prescribed fire need to provide for follow through to promote learning.

Extracting an injured firefighter – in 2 hours and 15 minutes

Las Conchas Fire extractionThe Wildfire Lessons Learned Center has released a video documenting the extraction of an injured firefighter from the 2011 Las Conchas Fire in northern New Mexico. Kenny Lovell of the Craig Interagency Hotshots is interviewed in the video and tells his story of being seriously injured, treated, and transported after being hit by a rolling rock. He suffered a broken pelvis, a broken fibula, and a large hematoma.

The title of the video, ROCK! Firefighter Extraction Success Story, describes the incident as a success. It was, in the sense that the Hotshot crew had access to equipment which was transported to the accident scene to treat and package the victim, there were several EMTs on the crew, the Hotshots had drilled for similar incidents, a helicopter with short haul capability was available, and 5 months later Mr. Lovell returned to work on the Hotshot crew. All that is great and the Hotshots and the helitack crew deserve praise for accomplishing what they did with the resources that were available..

Having said that, it is still troubling that 2 hours and 15 minutes elapsed before Mr. Lovell departed the accident scene in a helicopter, and 30 minutes later he arrived at a hospital. On the Deer Park fire in 2010 a firefighter with a broken femur was on the ground for 4 hours and 23 minutes before he was transported in a helicopter. And firefighter Andrew Palmer, who bled to death from a broken femur suffered on a fire in 2008, spent 2 hours and 51 minutes at the accident scene before he was extracted via hoist on a Coast Guard helicopter.

Agencies who place firefighters in remote areas should realize they have the ethical responsibility to supply the training, equipment, and aviation resources to at least begin transporting by air a seriously injured firefighter within an hour. I am surprised that OSHA has not cited the federal agencies for this. Of course getting injured firefighters to an appropriate hospital within the Golden Hour would be ideal, but depending on the distance involved that could be difficult. A helicopter with short haul capability can be helpful, but it is not the quickest or most efficient method for extracting an injured person. It involves several steps, especially, like in this case, when the helicopter responds to the scene without being fully configured for short haul.

Several agencies have helicopters with hoists which can quickly extract and then transport injured personnel from remote locations, including CAL FIRE, Los Angeles County Fire Department, and the Coast Guard. If the other federal and state agencies decided to take that step, it would not have to be a trial program with one helicopter like the U.S. Forest Service night flying helicopter effort this year, because other agencies have been using hoists (and night vision goggles) for decades,

“The organization is ethically and morally obligated to put an EMS program in place that is supported by the organization, and given the standardized training and equipment to make the program succeed.”

The above is from the 2010 facilitated learning analysis for the Deer Park Fire extraction, quoting a Senior Firefighter/Paramedic on the Sawtooth Helitack Crew.


Thanks go out to Brit

Report on fatal engine rollover on Montezuma Fire

Montezuma fire, fatality engine


Montezuma fire, fatality engine
Engine rollover fatality that occurred June 9, 2012 on the Montezuma Fire in Arizona.

The recently released 2012 Incident Review Summary mentioned a report that we were not aware had been released — the engine rollover fatality that occurred June 9, 2012 on the Montezuma Fire in Arizona. Killed in the accident was the Bureau of Indian Affairs engine boss, Anthony Polk, 31, of Yuma, Arizona. Two crewmembers were injured, one very seriously.

The three-person crew was en route to their assignment that morning. The AD crewmember driving was in his first fire season and had started work five days before. He received a valid Federal Motor Vehicle Operator’s ID card on May 3, 2012 about a month before he started work.

Below is an excerpt from the report:

Approximately 0745-0800 – The engines left the spike camp with Engine 1252 in the lead. Engine 6351 followed Engine 1252. Engine 6351 was being driven by Crewmember 2. Crewmember 1 occupied the middle seat, and the ENGB occupied the passenger side of the engine. The engines headed south on Indian Reservation Route 19. The engines drove up a moderate grade for the first couple of miles, crested the hill, and then started down a slight decline.

Approximately 0800 – The driver (Crewmember 2) stated that as they were driving and without prompting, the ENGB passed Crewmember 2 a bottle of water that had been on the dashboard on the passenger side where Crewmember 2 had previously been sitting. Crewmember 2 took the bottle and put it between his legs. The ENGB passed Crewmember 2 a second bottle of water and told Crewmember 2 to put the bottle behind his back.

As Crewmember 2 put the water bottle behind the back of his seat, he drifted off the right hand side of the road. He tried to steer the engine back onto the road, but overcorrected and went across both lanes of the road into the dirt on the other side. The engine flipped forward, landing with the weight on the hood and cab. The engine bounced, landed on its wheels and coasted across the highway (from east to west), coming to rest on the west side of the highway.

Findings, from the report:

  • The driver (Crewmember 2) was an AD Employee who was on his first off-unit fire assignment.
  • The driver (Crewmember 2) had no previous experience driving an engine.
  • The driver (Crewmember 2) was distracted, as water bottles were passed to him while he drove Engine 6351 on Indian Reservation Route 19.
  • No manual direction exists within the Bureau of Indian Affairs to ensure employees are qualified to drive Type 6 and larger engines.
  • Indian Reservation Route 19 is a relatively narrow road with no shoulder. The drop off from the paved surface to dirt is 4 to 6 inches. There is no “rumble strip” in place to alert the driver to the outside edge of the road surface.
  • Engine 6351 is a Chevrolet C-5500 engine platform (Model 52) rated as 19,500 GVW that has unique road handling characteristics that differ from the average sedan or pickup.
    • 1. While this vehicle does not have a CDL requirement, the weight of the vehicle (19,500 GVW) contributes to its unique road handling characteristics.
    • 2. The front axle width is approximately 15” wider than standard size vehicles. The axle width results in the vehicle encountering road surface irregularities differently than a vehicle with a narrower axle width.

Report released on prescribed fire burn injury

Burned pants

Burned pantsA Lessons Learned report has been released for a serious burn injury that occurred on the Saddle Salvage Natural Fuels burn unit, a prescribed fire somewhere in the Northwest. Oddly, neither the agency or even the state were identified, but the injured firefighter was eventually transferred to Harborview Burn Center in Seattle.

Briefly, a firefighter’s Nomex pants caught fire while he was using a drip torch to ignite vegetation during a black-lining operation. He suffered second and third degree burns over 20‐25% of his body, both legs and the left hand. He spent five weeks at the burn center but is now back to work on light duty. A full recovery is expected.

The report found that the management of the response to the injury went very well. Quite a bit went right.

A lab analysis of the protective clothing worn by the victim indicated that fuel was present on his pants and boots. Some of the fuel may have been deposited onto the clothing the previous day during ignition operations. Nomex contaminated with torch fuel is flammable even with small amounts of fuel and a low ratio of gas to diesel (1:5 gas to diesel) mixture.

The drip torch was inspected later at the Missoula Technology Development Center. Investigators found that the breather (vent) tube was in the torch but not attached to the breather tube screw. If the breather tube was disconnected from the breather tube screw during use, and the breather screw was open, fuel would drip from the screw.

A lab analysis of the drip torch fuel mix was completed. The analyzed torch fuel was not drawn from the injured employee’s torch, but did come from another torch that was used on the burn unit. Investigators concluded that the fuel was approximately a 1:1 gas/diesel mixture, which is a much higher concentration of gasoline than is specified in the U.S. Forest Service Health and Safety Code Handbook.

Report released on engine accident in northern California

Berry Point Fire engine accident
Berry Point Fire engine accident. Photo from the report.

A Facilitated Learning Analysis has been released for a non-injury accident that occurred in northern California, August 11, 2012. An engine from the Klamath National Forest ended up partially off of a dirt road after a soft shoulder gave way under the rear tires.

Berry Point Fire engine accident
Berry Point Fire engine accident. Photo from the report.

No one was injured and the engine only had very minor damage. Here is an excerpt from the report, picking up after the engine stabilized:

…The captain assessed the scene for safety and ordered the crew to exit the vehicle with most of the crew leaving the vehicle on the uphill side. I then dumped the water out of my tank to prevent possibility of continued rollover due to the soft pack. After the certified mechanic and I did a damage assessment investigation, we found the only damage was the petcock on the bottom of the pump was broken off. We had spares on board since this may happen occasionally on backwoods roads.

Report released for engine burnovers and entrapment on North Pass Fire

E-2 after the burnover
E-2 after the burnover. Photo from the report.

A Facilitated Learning Analysis has been released for the engine burnovers and entrapments that occurred on the North Pass Fire on the Mendocino National Forest in northern California, August 25, 2012.

You can read the entire report (large 3.8MB file), but here is a very brief summary. On August 18,2012, five Type 3 Engines from municipal fire departments in southern California were working as a Type 3 Engine Strike Team with the assignment that day of securing a dozer line. Due to dense vegetation along the dozer line, and a lack of information about their situation, they were surprised when a spot fire caused by a burning tree resulted in a fire that overran their position.

E-2 at the burnover site, before the incident and before turning around
E-2 at the burnover site, before the accident and before turning around. Photo from the report.

The crew from E-2 dismounted to assist with the spot fire, leaving the engine operator to button it up, disconnect hoses, and move it to assist with the spot fire at another location along the dozer line. The fire approached the engine before the operator was able to relocate the engine. He decided to run down the dozer line to escape, telling a hand crew after he reached safety, “F*** my engine burned up…. F*** my engine burned up!” Hand-crew members responded, “It’s fine, it’s fine. You’re alive so it’s fine.”

A second engine was also burned over, according to the report:

At the same time fire is engulfing E-2, E-5 finds their egress cut off by the flames now lying over the dozer line. E-5 was then forced to withdraw to a safe area. Capt. E-5 notifies ST-1C STEN they are remaining at their current location and requests permission to fire out the area around them. ST-1C STEN tells them, “Do what you need to do.” The crew of E-5 pre-treats the area around them using Class A foam, depleting their water supply. E-5 then deploys thermal curtains, and they seek shelter in the apparatus as the fire burns around them.

After the burnovers the strike team was sent to a USFS work station. The Strike Team Leader reported to a Ground Support Unit Leader who escorted them to the Incident Base. After receiving medical evaluations, all personnel were cleared by the Medical Unit and received no injuries.

Below are excerpts from the lessons learned, as shared by the facilitated learning analysis participants:

  • “Try to think more three-dimensionally. I really didn’t see/perceive the layout of the road, the green, or the fire. It would of helped to realize the danger there.”
  • “Maybe a picture from the air.”
  • ”I wish I’d known I had a qualified faller. Don’t know that I would of used them.” [to cut down the tree throwing out burning embers that caused the spot fire.]
  • “Had I perceived the danger, I wish I’d thought twice about the assignment for E-2.”
  • “I will definitely request more 800 MHz radios.”
  • From the Division Supervisor: “It would have been more appropriate to recognize that their (ST-1C) specialties were in other areas of firefighting and take the time to give them a more thorough briefing on the assignment rather than handing them off to be briefed by ST-2C STEN.”
  • “Walking through it afterward, E-2 was in perfect alignment with the draw, but of course you couldn’t see with all of the vegetation.”
  • From Capt. E-1: “Should of used a faller to drop the problem tree in the first place. Use the professionals.”
  • And from the same Capt: “There are all these other resources that we don’t normally deal with, like fallers, inmate crews and dozers. We had resources we could have used, but I just didn’t have the experience to think to ask for them.”

Excerpts of observations from the FLA team members:

  • The participants believe the division was large and complex. Geographically the division stretched over 5 to 7 miles of line.
  • The participants felt complexity and scope of the division complicated communications over the assigned tactical channel. Early on in the shift it was identified that communications were difficult. To mitigate it, ST-1C began using their 800 MHz for intra-crew communications. One difficulty was that not everyone had both radios. Some had the 800 MHz, and some had a VHF radio, but not everyone had both. Every member should have the same type of communication capability.
  • FLA team members and participants acknowledged that utilizing an unassigned tactical frequency on an incident is against several policies & guidelines.

USFS releases report on Steep Corner Fire fatality

Anne Veseth
Anne Veseth. Photo from the report.

The U.S. Forest Service has released their Serious Accident Investigation Report on the fatality of Anne Veseth, which occurred on the Steep Corner Fire 56 miles northeast of Orofino, Idaho August 12, 2012. The fire was on private property and was being managed by the Clearwater‐Potlatch Timber Protective Association (CPTPA). Ms. Veseth, in her second season working as a firefighter for the USFS, was killed when she was struck by a falling 150-foot tall fire-weakened green cedar tree. The tree fell on its own and was 13 inches in diameter where it struck her.

The USFS report came out a few days after OSHA issued a citation to the organization managing the fire, the Clearwater-Potlatch Timber Protective Association (CPTPA). The citation comes with a “Notification of Penalty”, fines totaling $14,000. OSHA also issued a Notice of Unsafe or Unhealthful Working Conditions to the U.S. Forest Service, but without a monetary penalty. Wildfire Today summarized the OSHA actions on February 12.

Here is an excerpt from the just-released USFS report:

****

“Analysis and Conclusion

“The cause of this accident was that a green cedar tree, weakened by fire, fell and struck a firefighter in the head. It fell with a force far greater than the design limits of any hardhat could withstand. This tragedy resulted from the chance alignment of certain conditions: an emergency response to control a wildland fire, which required the presence of firefighters in an area where fire‐weakened trees could fall on their own with little or no warning. The SAI team concluded that the convergence of these events – in a very specific way and with very specific timing – resulted in a fatal accident. Slight differences in any number of factors could have led to drastically different results.

“Firefighters faced the same choice on this fire as they do on almost every fire: engage the fire and expose firefighters to a certain set of risks in order to control the fire, or don’t engage the fire and don’t control it, knowing that such a decision often poses a wider range of risks to firefighters and the public. Firefighters made the same basic risk decision on the Steep Corner Fire as they do routinely on most fires: to engage the fire and attempt to control it, knowing that firefighters would be exposed to hazards during suppression efforts.

“On the day of the accident, after the implementation of safety mitigation measures, the firefighting professionals involved in the Steep Corner Fire reasoned the risks of engaging and suppressing the fire to be acceptable. After considerable review of the incident, including the leadership, qualifications, interagency cooperation, fuels, weather, incident management organization, and local policies, the SAI Team concluded that the judgments and decisions of the firefighters involved in the Steep Corner Fire were appropriate. Firefighters all performed within the leaders’ intent and scope of duty, as defined by their respective organizations. The team did not find any reckless actions or violations of policy or protocol.

“On August 11, the day before the fatal accident, two Forest Service resources decided to limit their acceptance of risk on the Steep Corner Fire. Both the IHC and the E‐31 crew identified necessary safety mitigations. The IHC chose not to engage. The E‐31 crew disengaged and indicated they would not return to the fire until mitigation measures were implemented.

“C‐PTPA took these events seriously and subsequently addressed the recommended mitigation measures. Personnel became the “adapters” that allowed C‐PTPA and the Forest Service, two organizations with very different natural resource management mandates, to functiontogether. Mitigation measures included ordering more firefighting resources, adding line overhead and a radio repeater, and using contract fallers to fell hazard trees ahead of those digging fireline. The morning of August 12, the E‐31 crew decided to re‐engage when it became clear C‐PTPA was addressing their safety concerns. The IHC was already reassigned to anotherfire and did not return. In general, firefighters expressed their impressions that Saturday was a bad day but Sunday (before the accident) was much better, in terms of organization of the fire and mitigation of the hazards.”

(end of excerpt)

****

The 38-page report only has two recommendations. One is to introduce the LCES (Lookouts, Communications, Escape Routes, Safety Zones) concept into the National Wildfire Coordinating Group’s curriculum for use in disciplines other than fire management. The other is: “Occupational Safety and Health Office should develop a methodology for effectively teaching non‐fire workers the concepts related to hazard tree identification, scouting an area, and determining escape routes and safety zones for overhead hazards”.

An opinion

Several things about the incident and the report are troubling, but one item in the report stood out (emphasis added):

This tragedy resulted from the chance alignment of certain conditions: an emergency response to control a wildland fire, which required the presence of firefighters in an area where fire‐weakened trees could fall on their own with little or no warning.

Perhaps it is just an unfortunate choice of words chosen by the primary author which somehow was missed by the large number of people who probably reviewed the report before it was released. Giving them the benefit of the doubt, maybe they didn’t really mean to imply that firefighters are REQUIRED to perform an action on a fire simply because the fire is uncontrolled, even “where fire‐weakened trees could fall on their own with little or no warning”.

Someone might say that trees could fall during suppression action on most timber fires. Right. However on this fire, the large number of falling trees was identified the previous day, when a Hotshot crew refused to be assigned to the fire because of falling trees and many other unmitigated hazards, saying in a SAFENET report filed three days later that they “had huge concerns about the number of snags burning”. An engine crew left the fire for similar reasons that afternoon, but returned the next day after being assured that the hazards had been mitigated.

Firefighters are not REQUIRED to perform a task on a fire if there are known extraordinary hazards that cannot mitigated. We are talking about trees, grass, brush, or houses…. that will all grow back. Firefighters can’t.

Maybe it is just an unfortunate choice of words.

NPS releases report on Lassen National Park’s Reading Fire

Reading Fire
Reading Fire
Reading Fire. Photo by Lassen National Park.

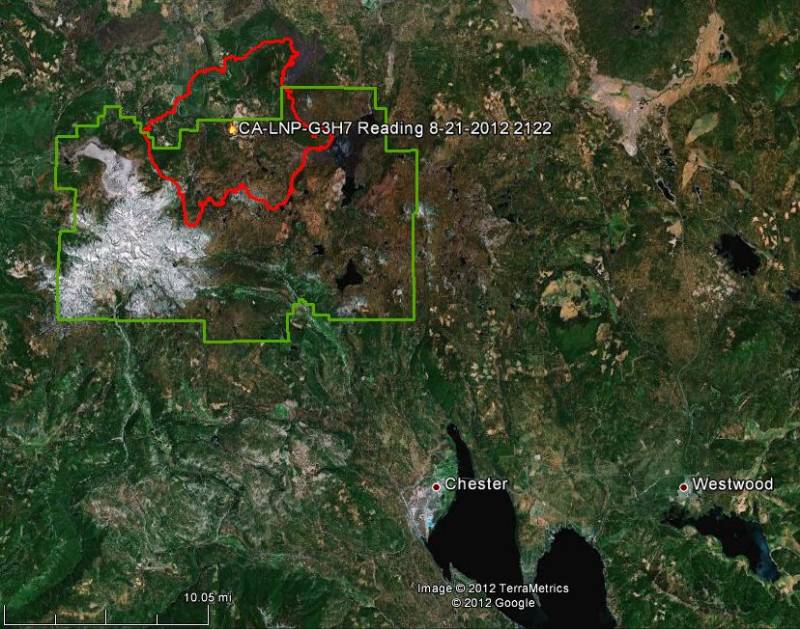
The National Park Service has released a report about last summer’s Reading Fire in Lassen Volcanic National Park in California which, after being monitored for two weeks and burning 95 acres, grew to 28,079 acres, escaping the park boundaries. The fire started from a lightning strike on July 23, 2012 and was contained on August 22. For the first two weeks it was managed under a “Wildland Fire for Resource Benefit” strategy.

Reading Fire, final perimeter
Final perimeter (in red) of the Reading Fire. The green line is the boundary of Lassen Volcanic National Park.

The expectation was that they could stop the fire when it reached the Lassen National Park Highway, about a mile north of the point of origin. On August 6 when the fire was 140 acres the Type 4 Incident Commander transitioned to a Type 3 IC. Later in the day the fire ran for about a mile and a half, blowing right across the 2-lane highway. Then a Type 2 Incident Managment Team was ordered, which eventually transitioned to a Type 1 IMTeam on August 13. When the fire was contained it had burned 11,071 acres of US Forest Service land outside the park boundaries and 75 acres privately owned, for a total of 28,079 acres. By August 23 the National Park Service had spent $15,875,495 observing, managing, and later suppressing the fire.

As we have stated before, managing a fire with your hands tied by utilizing little to no aggressive suppression action, is extremely difficult, requiring an extraordinary amount of skill, knowledge, expertise, experience, and luck. Especially if the fire starts in mid-July, leaving 6 to 12 weeks of weather ahead that is conducive to rapid fire spread. Few people can do this. It is impossible to predict accurately how weather will affect a fire more than 10 days ahead.

Here are some some excerpts from the 53-page report:
Continue reading